


- -22.1%

Recommended price

€14.18

 Richiedi info sul prodotto
Estimated delivery: 2-5 working days

Information on returns and shipments

Payment methods


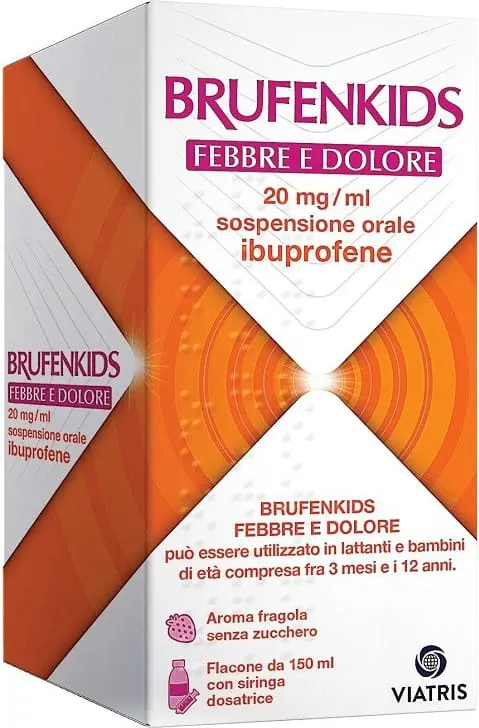
Antipyretic and analgesic drug indicated for infants and children aged between 3 months and 12 years.
Symptomatic treatment of fever and mild to moderate pain.
Each ml of oral suspension contains:
Active ingredient: ibuprofen 20 mg;
Excipients: sodium benzoate (E-211), anhydrous citric acid, sodium citrate, sodium saccharin, sodium chloride, hypromellose, xanthan gum, maltitol syrup, strawberry flavoring, azorubine (E-122), glycerol (E-422), purified water.
The dosage is structured according to the age and weight of the subject to be treated. This medicine is indicated for infants and children aged between 3 months and 12 years. The graduated scale on the body of the syringe clearly shows the marks for the two different dosages: the 2.5 ml mark corresponding to 50 mg of ibuprofen and the 5 ml mark corresponding to 100 mg of ibuprofen.
For the treatment of pain and fever, the daily dose of 20–30 mg/kg of body weight can be administered according to the following schedule.
| AGE | WEIGHT (Kg) | DOSE |
| 3 months – 6 months | 5 - 7.7 | 2.5ml 3 times a day |
| 6 months – 12 months | 7.8 – 10 | 2.5ml 3 times a day |
| 1 year – 3 years | 11 - 15 | 5ml 3 times a day |
| 4 years – 6 years | 16 - 20 | 7.5ml 3 times a day |
| 7 years – 9 years | 21 - 29 | 10ml 3 times a day |
| 10 years – 12 years | 30- 40 | 15ml 3 times a day |
Undesirable effects can be minimised by using the lowest effective dose for the shortest duration necessary to control symptoms (see section 4.4). The action of the medicine lasts up to 8 hours, but the doctor may adopt shorter intervals if necessary, but in any case not exceeding the maximum daily dose of 30 mg/kg. In infants aged between 3 and 5 months, a doctor should be consulted if symptoms persist for more than 24 hours or in case of worsening of symptoms. If use of the medicine is necessary for more than 24 hours, the doctor should be consulted. 3 days in infants and children over 6 months of age and in adolescents, or in case of worsening of symptoms, a doctor must be consulted.
For oral administration, using the measuring syringe supplied with the medicine. To obtain a more rapid onset of action, the dose can be taken on an empty stomach. In patients with gastric sensitivity, it is recommended to take FROBENKIDS FEVER AND PAIN with food. With FROBENKIDS FEVER AND PAIN, a transient burning sensation in the mouth or throat may occur; Make sure the bottle is thoroughly shaken before use.
Hypersensitivity to the active substance or to any of the excipients listed in paragraph 6.1. Children under 3 months of age or weighing less than 5 kg. Subjects with hypersensitivity to acetylsalicylic acid or other analgesics, antipyretics, non-steroidal anti-inflammatory drugs (NSAIDs), particularly when hypersensitivity is associated with nasal polyps, angioedema and/or asthma. Severe or active peptic ulcer. Severe hepatic insufficiency. Severe renal insufficiency (glomerular filtration rate less than 30 ml/min). Severe heart failure (NYHA class IV). Severe dehydration (caused by vomiting, diarrhea or insufficient fluid intake). History of gastrointestinal bleeding or perforation, related to previous active therapy, or history of recurrent peptic ulcer/haemorrhage (two or more distinct episodes of proven ulceration or bleeding). Patients with medical conditions that increase bleeding tendency. During the third trimester of pregnancy (see section 4.6).
The use of FROBENKIDS FEVER AND PAIN in conjunction with other NSAIDs, including selective COX-2 inhibitors, should be avoided due to an increased risk of ulceration or bleeding (see section 4.5). As with other NSAIDs, ibuprofen may mask signs of infection. Headache may occur with prolonged use and should not be treated by increasing the dosage of the medicinal product. Gastrointestinal and central nervous system adverse reactions may be increased with the use of NSAIDs and concomitant alcohol consumption. Elderly Elderly patients have an increased frequency of adverse reactions to NSAIDs, especially gastrointestinal bleeding and perforation, which may be fatal (see section 4.2). Gastrointestinal bleeding, ulceration and perforation Gastrointestinal bleeding, ulceration and perforation, which can be fatal, have been reported with all NSAIDs at anytime during treatment, with or without warning symptoms or a previous history of serious gastrointestinal events. The risk of gastrointestinal bleeding, ulceration or perforation is higher with increasing NSAID doses, in the elderly and in patients with a history of ulcer, particularly if complicated with haemorrhage or perforation (see section 4.3). These patients should start treatment on the lowest available dose. For these patients, and also for patients taking low-dose aspirin or other drugs that may increase the risk of gastrointestinal events, concomitant use of gastroprotective agents (misoprostol or proton pump inhibitors) should be considered (see below and section 4.5). Patients with a history of gastrointestinal toxicity, particularly when elderly, should report any unusual gastrointestinal symptoms (especially gastrointestinal bleeding), particularly in the initial stages of treatment. Caution should be exercised in patients receiving concomitant medications which could increase the risk of ulceration or bleeding, such as oral corticosteroids, anticoagulants such as warfarin, selective serotonin reuptake inhibitors (SSRIs), or antiplatelet agents such as acetylsalicylic acid (see section 4.5). If gastrointestinal bleeding or ulceration occurs in patients taking FROBENKIDS FEVER AND PAIN, the treatment should be discontinued. NSAIDs should be administered with caution to patients with a history of gastrointestinal disease (ulcerative colitis, Crohn's disease) as these conditions may be exacerbated (see section 4.8). Use with caution in patients with coagulation defects. Cardiovascular and cerebrovascular effects Appropriate monitoring and advice are necessary in patients with a history of hypertension and/or mild to moderate congestive heart failure as fluid retention and edema have been reported in association with NSAID therapy. Clinical trials suggest that use of ibuprofen, particularly at high doses (2400 mg/day), may be associated with a small increased risk of arterial thrombotic events (for example, myocardial infarction or stroke). Overall, epidemiological studies do not suggest that low-dose ibuprofen (for example, 1200 mg/day) is associated with an increased risk of arterial thrombotic events. Patients with uncontrolled hypertension, congestive heart failure (NYHA class II-III), established ischemic heart disease, peripheral arterial disease, and/or cerebrovascular disease should be treated with ibuprofen only after careful consideration, and high doses (2400 mg/day) should be avoided. Careful consideration should also be exercised before initiating long-term treatment in patients with risk factors for cardiovascular events (e.g., hypertension, hyperlipidaemia, diabetes mellitus, smoking), particularly if high doses (2400 mg/day) of ibuprofen are required. Dermatological effects Serious skin reactions, some of them fatal, including exfoliative dermatitis, Stevens-Johnson syndrome, and toxic epidermal necrolysis, have been reported very rarely in association with the use of NSAIDs (see section 4.8). Patients appear to be more sensitive to ibuprofen in the early stages of therapy. High risk: the onset of the reaction occurs in most cases within the first month of treatment. FROBENKIDS FEVER AND PAIN should be discontinued at the first appearance of skin rash, mucosal lesions, or any other sign of hypersensitivity. Renal effects When initiating treatment with ibuprofen, caution should be exercised in patients with significant dehydration. Long-term use of ibuprofen, as with other NSAIDs, has led to renal papillary necrosis and other pathological renal changes. In general, the habitual use of analgesics, especially combinations of different analgesic active ingredients, can lead to permanent renal damage, with the risk of developing renal failure (analgesic nephropathy). Renal toxicity has been observed in patients in whom renal prostaglandins have a compensatory role in maintaining renal perfusion. The administration of NSAIDs in these patients may be contraindicated. NSAIDs may cause a dose-dependent reduction in prostaglandin formation and, as a secondary effect, renal blood flow. This can quickly lead to renal failure. Patients most at risk of these reactions are those with reduced renal function, heart failure, liver dysfunction, the elderly, and all patients taking diuretics and ACE inhibitors. Discontinuation of NSAID therapy is usually followed by recovery to the pre-treatment state. In case of prolonged use, monitor renal function, particularly in cases of diffuse lupus erythematosus. In dehydrated children and adolescents, there is a risk of impaired renal function. Respiratory disorders FROBENKIDS FEVER AND PAIN should be administered with caution in patients with bronchial asthma, chronic rhinitis, or current or previous allergic diseases because bronchospasm, urticaria, or angioedema may occur. The same applies to those who have experienced bronchospasm after using aspirin or other NSAIDs. Hypersensitivity reactions Analgesics, antipyretics, and nonsteroidal anti-inflammatory drugs can cause potentially serious hypersensitivity reactions (anaphylactoid reactions), even in subjects not previously exposed to this type of drug. The risk of hypersensitivity reactions after taking ibuprofen is greater in subjects who have experienced such reactions after using other analgesics, antipyretics, and nonsteroidal anti-inflammatory drugs and in subjects with bronchial hyperreactivity (asthma), hay fever, nasal polyps, chronic obstructive respiratory disease, or previous episodes of angioedema (see sections 4.3 and 4.8). Hypersensitivity reactions may present as asthma attacks (so-called analgesic asthma), Quincke's edema, or urticaria. Severe hypersensitivity reactions (e.g., anaphylactic shock) have been observed rarely. At the first signs of a hypersensitivity reaction after ibuprofen administration, treatment should be discontinued. Medically assisted measures should be initiated by specialized medical personnel, in line with the symptoms. Reduced cardiac, renal, or hepatic function Particular caution should be exercised when treating patients with reduced cardiac, hepatic, or renal function, as the use of NSAIDs may lead to deterioration of renal function. The habitual concomitant use of several painkillers may further increase this risk. In patients with reduced cardiac, hepatic, or renal function, it is advisable to use the lowest effective dose for the shortest duration of treatment and to periodically monitor clinical and laboratory parameters, especially in case of prolonged treatment (see section 4.3). Haematological effects Ibuprofen, like other NSAIDs, may cause renal impairment. inhibit platelet aggregation and has been shown to prolong bleeding time in healthy subjects. Aseptic meningitis. On rare occasions, aseptic meningitis has been observed in patients treated with ibuprofen. Although this is more likely to occur in patients with systemic lupus erythematosus and related connective tissue diseases, it has also been observed in patients without concomitant chronic diseases (see section 4.8). Since ocular changes have been observed in animal studies with nonsteroidal anti-inflammatory drugs, periodic ophthalmological checks are recommended in case of prolonged treatment. The use of FROBENKIDS FEVER AND PAIN, as with any drug that inhibits the synthesis of prostaglandins and cyclooxygenase, is not recommended in women attempting to conceive (see section 4.6). The administration of FROBENKIDS FEVER AND PAIN should be suspended in women who have fertility problems or who are undergoing fertility investigations. Important information about some of the excipients FROBENKIDS FEVER AND PAIN contains: § maltitol. Patients with rare hereditary problems of fructose intolerance should not take this medicine. § E122 Azorubine. May cause allergic reactions.
Ibuprofen (like other NSAIDs) should be used with caution in combination with: corticosteroids: increased risk of gastrointestinal ulceration or bleeding (see section 4.4); anticoagulants: NSAIDs may increase the effects of anticoagulants, such as warfarin (see section 4.4). Patients treated with coumarins should be monitored; other NSAIDs: these substances may increase the risk of adverse reactions affecting the gastrointestinal tract (see section 4.4); Acetylsalicylic acid: Concomitant administration of ibuprofen and acetylsalicylic acid is generally not recommended due to the potential for increased adverse effects. Experimental data suggest that ibuprofen may competitively inhibit the effect of low-dose acetylsalicylic acid on platelet aggregation when the two drugs are administered concomitantly. Although there are uncertainties regarding the extrapolation of these data to the clinical situation, the possibility that regular, long-term use of ibuprofen may reduce the cardioprotective effect of low-dose acetylsalicylic acid cannot be excluded. No clinically relevant effect is considered likely following occasional use of ibuprofen (see section 5.1). However, it is advisable not to combine ibuprofen with aspirin or other NSAIDs; Antiplatelet agents and selective serotonin reuptake inhibitors (SSRIs): increased risk of gastrointestinal bleeding (see section 4.4); Diuretics, ACE inhibitors and Angiotensin II antagonists: NSAIDs may reduce the effect of diuretics and other antihypertensive drugs. Diuretics may also increase the risk of nephrotoxicity associated with NSAIDs. In some patients with compromised renal function (e.g. dehydrated patients or elderly patients), co-administration of an ACE inhibitor or an angiotensin II antagonist and agents that inhibit the cyclooxygenase system may lead to further deterioration of renal function, including possible acute renal failure, which is usually reversible. These interactions should be considered in patients taking FROBENKIDS FEVER AND PAIN concomitantly with ACE inhibitors or angiotensin II antagonists. Therefore, this combination should be administered with caution, especially in elderly patients. Patients should be adequately hydrated, and renal function monitoring should be considered after initiation of concomitant therapy and periodically thereafter; lithium: concomitant administration of lithium and NSAIDs causes increased plasma lithium levels due to reduced elimination, with the possibility of reaching the toxic threshold. If this combination is necessary, serum lithium levels should be monitored in order to adapt the lithium dosage during concomitant treatment with ibuprofen; methotrexate: NSAIDs may inhibit the tubular secretion of methotrexate and reduce its clearance, resulting in an increased risk of toxicity; aminoglycosides: NSAIDs may decrease the excretion of aminoglycosides; cardiac glycosides: NSAIDs may exacerbate heart failure, reduce the glomerular filtration rate, and increase plasma cardiac glycoside levels; cholestyramine: Concomitant administration of ibuprofen and cholestyramine may reduce the absorption of ibuprofen from the gastrointestinal tract. However, the clinical relevance of this interaction is unknown; ciclosporin: Increases the risk of nephrotoxicity with NSAIDs; Cox-2 inhibitors and other NSAIDs: Concomitant use with other NSAIDs, including selective cyclooxygenase-2 inhibitors, should be avoided due to the potential for additive effects (see section 4.4); plant extracts: Ginkgo Biloba may increase the risk of bleeding in association with NSAIDs; mifepristone: Due to the anti-prostaglandin properties of NSAIDs, a decrease in the efficacy of the medicinal product may theoretically occur. Limited evidence suggests that co-administration of NSAIDs on the day of prostaglandin administration does not adversely affect the effects of mifepristone or the prostaglandin on cervical ripening or uterine contractility and does not reduce the clinical efficacy of the drug on pregnancy termination; quinolone antibiotics: Animal data indicate that NSAIDs may increase the risk of convulsions associated with quinolone antibiotics. Patients taking NSAIDs and quinolones may have an increased risk of developing convulsions; sulfonylureas: NSAIDs may enhance the effect of sulfonylureas. Rare cases of hypoglycemia have been reported in patients treated with sulfonylureas who were taking ibuprofen; tacrolimus: possible increased risk of nephrotoxicity when NSAIDs are administered with tacrolimus; zidovudine: increased risk of haematological toxicity when co-administered with NSAIDs. There is evidence of an increased risk of haemarthrosis and haematoma in HIV-infected haemophiliac patients receiving concomitant treatment with zidovudine and other NSAIDs; ritonavir: possible increase in NSAID concentrations; probenecid: slows the excretion of NSAIDs, with possible increase in their plasma concentrations; CYP2C9 inhibitors: concomitant administration of ibuprofen and CYP2C9 inhibitors may increase exposure to ibuprofen (CYP2C9 substrate). In a study with voriconazole and fluconazole (CYP2C9 inhibitors), an increased exposure to S(+)-ibuprofen of approximately 80% to 100% was observed. Consideration should be given to reducing the ibuprofen dose when strong CYP2C9 inhibitors are administered concomitantly, particularly when high doses of ibuprofen are administered with voriconazole or fluconazole.
The undesirable effects observed with ibuprofen are generally common with other analgesics, antipyretics, and non-steroidal anti-inflammatory drugs. Gastrointestinal disorders The most commonly observed adverse events are gastrointestinal in nature. Peptic ulcers, perforation, or gastrointestinal bleeding, sometimes fatal, particularly in the elderly, may occur (see section 4.4). Gastrointestinal perforation has been observed rarely with the use of ibuprofen. Nausea, vomiting, diarrhea, flatulence, constipation, dyspepsia, abdominal pain, melaena, haematemesis, ulcerative stomatitis, exacerbation of colitis and Crohn's disease have been reported following administration of FROBENKIDS FEVER AND PAIN (see section 4.4). Less frequently, gastritis, epigastric pain, and heartburn have been observed. Pancreatitis has also been observed very rarely. A transient burning sensation in the mouth or throat may occur with FROBENKIDS FEVER AND PAIN. Immune system disorders Hypersensitivity reactions have been reported following treatment with NSAIDs. These may consist of a) non-specific allergic reaction and anaphylaxis, b) respiratory tract reactions including asthma, including severe asthma, bronchospasm, or dyspnoea, or c) various skin disorders, including rashes of various types, pruritus, urticaria, purpura, angioedema, and, more rarely, exfoliative and bullous dermatitis (including Stevens-Johnson syndrome, toxic epidermal necrolysis, and erythema multiforme). Cardiac and vascular disorders: Edema, fatigue, hypertension, and cardiac failure have been reported in association with NSAID treatment. Clinical trials suggest that use of ibuprofen, particularly at high doses (2400 mg/day), may be associated with a small increased risk of arterial thrombotic events (for example, myocardial infarction or stroke) (see section 4.4). Other adverse events reported less frequently and for which causality has not necessarily been established include: Blood and lymphatic system disorders: leukopenia, thrombocytopenia, neutropenia, agranulocytosis, aplastic anaemia, and haemolytic anaemia. Psychiatric disorders: insomnia, anxiety, depression, confusional state, hallucinations. Effects on the nervous system and sense organs: headache, paraesthesia, dizziness, somnolence, optic neuritis. Infections and infestations: aseptic rhinitis and meningitis (especially in patients with pre-existing autoimmune disorders, such as systemic lupus erythematosus and mixed connective tissue disease) with symptoms of stiff neck, headache, nausea, vomiting, fever, or disorientation (see section 4.4). Exacerbation of infection-related inflammation (e.g., development of necrotising fasciitis) has been described. Respiratory, thoracic, and mediastinal disorders: bronchospasm, dyspnea, apnea. Eye disorders: rare cases of ocular alteration resulting in visual disturbances, toxic optic neuropathy. Ear and labyrinth disorders: impaired hearing, tinnitus, vertigo. Hepatobiliary disorders: altered liver function, liver failure, hepatitis, and jaundice. Skin and subcutaneous tissue disorders: bullous reactions, including Stevens-Johnson syndrome and toxic epidermal necrolysis (very rare), and photosensitivity reactions. In exceptional cases, serious skin infections and soft tissue complications may occur during varicella infection (see also "Infections and infestations"). Renal and urinary disorders: impaired renal function and toxic nephropathy in various forms, including interstitial nephritis, nephrotic syndrome, and renal failure. General disorders and administration site conditions: malaise, fatigue. Effects on the endocrine system and metabolism: decreased appetite. Reporting of suspected adverse reactions Reporting suspected adverse reactions that occur after authorization of the medicinal product is important, as it allows continued monitoring of the benefit/risk balance of the medicinal product. Healthcare professionals are asked to report any suspected adverse reactions via the national reporting system at http://www.agenziafarmaco.gov.it/it/responsabili.
Toxicity Signs and symptoms of toxicity have generally not been observed at doses less than 100 mg/kg in children or adults. However, in some cases, supportive treatment may be necessary. Children have been observed to show signs and symptoms of toxicity after ingestion of ibuprofen at doses of 400 mg/kg or greater. Symptoms Most patients who have ingested significant amounts of ibuprofen will experience symptoms within 4–6 hours. The most commonly reported symptoms of overdose include abdominal pain, nausea, vomiting, lethargy, and drowsiness. Central nervous system (CNS) effects include headache, tinnitus, dizziness, convulsions, and loss of consciousness. Nystagmus, metabolic acidosis, hypothermia, renal effects, gastrointestinal bleeding, coma, apnea, diarrhea, and central nervous system and respiratory depression have also been reported rarely. Disorientation, excitation, fainting, and cardiovascular toxicity including hypotension, bradycardia, and tachycardia have been reported. Renal failure and liver damage are possible in cases of significant overdose. Acute overdose is generally well tolerated when no other medications have been administered. Treatment There is no specific antidote for ibuprofen overdose. Treatment consists primarily of appropriate supportive measures; Particular attention should be paid to monitoring blood pressure, acid-base balance, and any gastrointestinal bleeding. Administration of activated charcoal should be considered within one hour of ingestion of a potentially toxic amount. Alternatively, gastric lavage should be considered within one hour of ingestion of a potentially life-threatening overdose in adults. Adequate diuresis should be ensured, and renal and hepatic function should be closely monitored. The patient should remain under observation for at least four hours following ingestion of a potentially toxic amount of the drug. Any occurrence of frequent or prolonged convulsions should be treated with intravenous diazepam. Other supportive measures may be necessary depending on the patient's clinical condition. For more information, contact your local poison control center.
Pregnancy: Inhibition of prostaglandin synthesis may adversely affect pregnancy and/or embryo/fetal development. Results of epidemiological studies suggest an increased risk of miscarriage, cardiac malformation, and gastroschisis after use of a prostaglandin synthesis inhibitor in early pregnancy. The absolute risk of cardiac malformations increased from less than 1% to approximately 1.5%. The risk is believed to increase with dose and duration of therapy. In animals, administration of prostaglandin synthesis inhibitors has been shown to result in increased pre- and post-implantation loss and embryo-fetal mortality. Additionally, an increased incidence of various malformations, including cardiovascular, has been reported in animals administered prostaglandin synthesis inhibitors during the organogenetic period. During the first and second trimesters of pregnancy, FROBENKIDS FEVER AND PAIN should not be administered unless clearly necessary. Se FROBENKIDS FEBBRE E DOLORE è usato da una donna in attesa di concepimento o durante il primo e secondo trimestre di gravidanza, la dose e la durata del trattamento devono essere mantenute le più basse possibili. Durante il terzo trimestre di gravidanza, tutti gli inibitori della sintesi delle prostaglandine possono esporre il feto a: tossicità cardiopolmonare (con chiusura prematura del dotto arterioso e ipertensione polmonare); disfunzione renale che può progredire a insufficienza renale con oligo–idroamnios; la madre e il neonato, alla fine della gravidanza, a: possibile prolungamento del tempo di sanguinamento, un effetto antiaggregante che può occorrere anche a dosi molto basse; inibizione delle contrazioni uterine risultanti in ritardo o prolungamento del travaglio. Conseguentemente FROBENKIDS FEBBRE E DOLORE è controindicato durante il terzo trimestre di gravidanza. Allattamento Nei pochi studi ad oggi disponibili, i FANS possono ritrovarsi nel latte materno in concentrazioni molto basse. I FANS, se possibile, devono essere evitati durante l'allattamento materno. Fertilità L'uso di Ibuprofene può compromettere la fertilità femminile e non è raccomandato nelle donne in attesa di concepimento. Nelle donne che hanno difficoltà a concepire o che sono oggetto di indagine sulla infertilità, si deve considerare l'interruzione del trattamento con ibuprofene.
Questo medicinale non richiede alcuna condizione particolare di conservazione.
Flacone da 150 ml con siringa dosatrice
This product has been on sale since 25/09/2017
In the last 30 days, the product's lowest price was 9,03 €

Estimated delivery: 2-5 working days


Estimated delivery: 2-5 working days

Estimated delivery: 2-5 working days

Estimated delivery: 2-5 working days

Estimated delivery: 2-5 working days
